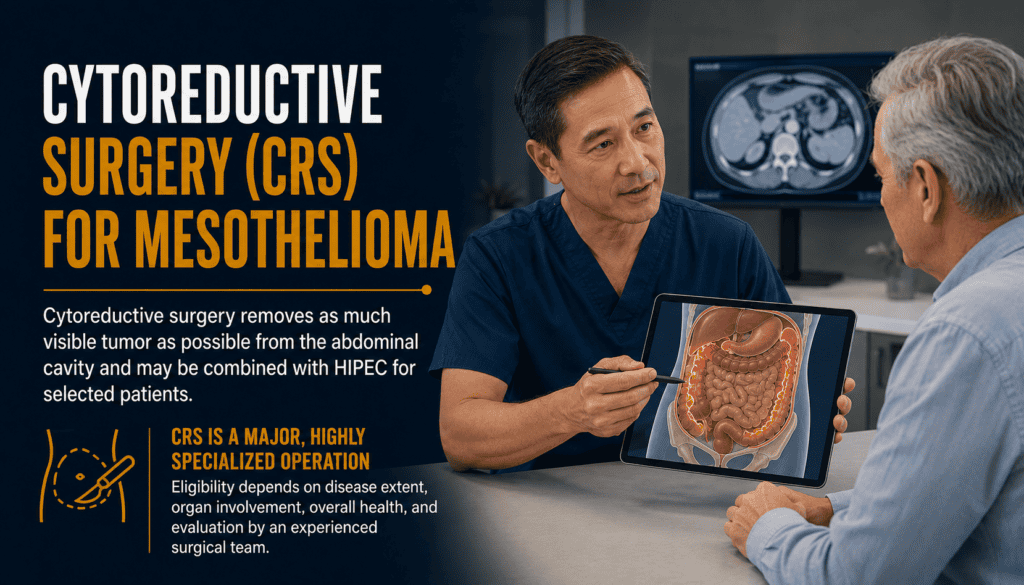
Cytoreductive Surgery (CRS) for Mesothelioma: Eligibility, HIPEC, Risks & Recovery
A patient and family guide to surgery for peritoneal mesothelioma, including how HIPEC fits into care.
Key point: Cytoreductive surgery is an extensive operation considered for selected patients. Its goal and risks must be discussed with a specialist; it is not a guaranteed cure.
What Is Cytoreductive Surgery?
Cytoreductive surgery (CRS) is an operation intended to remove as much visible cancer as safely possible. For malignant peritoneal mesothelioma, which develops in the lining of the abdomen, surgeons may remove tumor deposits from the peritoneum and, when necessary, affected tissue or organs. The extent depends on where disease is located and the patient’s health. Removing visible disease does not guarantee that microscopic cancer cells are gone.
CRS is different from surgery for pleural mesothelioma, which affects the lining around the lungs. The choice of operation must follow an accurate diagnosis and assessment by a specialist team.
| Term | Meaning |
|---|---|
| Cytoreduction | Removal of as much visible tumor as safely feasible |
| Peritoneum | Thin tissue lining the abdominal cavity and covering many organs |
| Complete cytoreduction | No visible tumor, or only very small residual deposits, depending on the scoring system |
| Microscopic disease | Cancer cells too small to see during an operation |
Who May Be Considered for CRS?
CRS is not appropriate for everyone. A specialist team considers the extent and distribution of disease, pathology, general health, nutritional status, other illnesses, and whether surgery is likely to remove enough tumor to offer a meaningful benefit. Imaging helps planning but cannot always reveal every tumor deposit. A surgeon may determine during an operation that complete cytoreduction is not safely possible.
Age alone should not decide eligibility. An older adult’s functional ability, goals, and operative risks deserve individualized consideration. Ask whether your case has been reviewed at a center experienced in peritoneal surface malignancies.
| Assessment | Why it matters |
|---|---|
| Pathology review | Confirms mesothelioma type and histology |
| CT or other imaging | Maps visible disease and possible spread |
| Functional and heart/lung evaluation | Estimates ability to tolerate major surgery |
| Nutrition and blood tests | Identifies problems to address before an operation |
| Patient goals | Balances potential benefit with recovery burden |
How CRS and HIPEC May Work Together
For selected patients with peritoneal mesothelioma, CRS may be followed during the same operation by hyperthermic intraperitoneal chemotherapy (HIPEC). After visible tumors are removed, a chemotherapy solution is circulated within the abdominal cavity for a protocol-defined period under controlled conditions. The specific drug, temperature, duration, and suitability vary by center and patient. HIPEC is intended to treat remaining microscopic disease; it cannot ensure that every cancer cell is eliminated.
CRS and HIPEC are not interchangeable. Some patients may not receive HIPEC because of medical risk or operative findings. Ask your team what evidence applies to your particular disease and what alternatives are available.
| Step | Purpose |
|---|---|
| Exploration | Assess disease distribution and operability |
| Cytoreduction | Remove visible tumors where safely possible |
| HIPEC, when appropriate | Expose the abdominal cavity to heated chemotherapy |
| Postoperative monitoring | Identify complications and support recovery |
Preparing for Surgery
Preparation usually includes specialist consultation, review of pathology and scans, assessment of medications, and discussion of expected hospitalization. Tell the team about blood thinners, supplements, allergies, prior abdominal surgery, and other health conditions. Do not stop prescribed medicines without instructions. If eating is difficult or weight has fallen, ask for oncology dietitian support before surgery.
Discuss fertility, ostomy possibilities, organ removal, pain control, and whether a caregiver will be needed after discharge. Make sure the surgeon explains both the planned procedure and what could change if the actual disease burden differs from imaging.
| Before the operation | Question to ask |
|---|---|
| Surgical plan | Which organs or tissues might need removal? |
| HIPEC plan | Is HIPEC expected, and could it be omitted? |
| Risk assessment | What are my individualized complication risks? |
| Hospital plan | Will I need intensive monitoring or rehabilitation? |
| Home preparation | What equipment or caregiver support should I arrange? |
Risks and Possible Complications
CRS, especially when combined with HIPEC, is major surgery. Potential complications include bleeding, infection, blood clots, bowel leak, ileus (temporary slowing of bowel movement), kidney injury, nutritional difficulties, and problems involving any organ operated on. Chemotherapy used during HIPEC can add drug-specific risks. Some patients require another operation, prolonged hospitalization, or intensive care; a small number die from complications. Your surgical team should explain its own experience and your individualized risk rather than offering a generic prediction.
Seek urgent medical assessment for severe or worsening abdominal pain, fever, chest pain, sudden shortness of breath, fainting, uncontrolled vomiting, significant bleeding, or a wound that becomes increasingly red or drains pus. Follow your discharge team’s specific instructions.
| Possible issue | What to discuss |
|---|---|
| Infection or bowel leak | Symptoms and emergency contact pathway |
| Blood clots | Prevention and warning signs |
| Kidney or blood-count effects | Monitoring after HIPEC, if used |
| Nutrition and bowel function | Eating plan and expected recovery |
| Unexpected organ removal | How this could affect daily life |
Hospital Stay and Recovery at Home
Recovery varies widely with the extent of surgery, complications, baseline health, and whether HIPEC was given. In the hospital, patients may receive intravenous fluids, pain relief, blood-clot prevention, and help walking. Bowel function may take time to return. Some people need temporary nutritional support, rehabilitation, or home nursing. Do not assume that another patient’s recovery schedule will apply to you.
At home, follow restrictions on lifting, driving, wound care, and medicines. Keep a list of symptoms and questions. Ask when to resume exercise, work, and ordinary activities, and whom to contact after hours. A caregiver can help coordinate transportation and meals while respecting the patient’s preferences.
| Recovery task | Practical action |
|---|---|
| Medication | Use the written discharge schedule; confirm changes |
| Wound | Follow cleaning and dressing instructions |
| Movement | Walk and increase activity only as advised |
| Nutrition | Report persistent nausea or inability to eat |
| Follow-up | Keep pathology, imaging, and surgical appointments |
Benefits, Limits, and Alternatives
For carefully selected patients with peritoneal mesothelioma, CRS with or without HIPEC may offer disease control and, in some cases, prolonged survival. Results reported by specialized centers can reflect selection of patients healthy enough for surgery and with disease that can be removed. They should not be treated as a personal prognosis. Some patients experience recurrence despite extensive surgery.
If CRS is not appropriate, the care team may discuss systemic therapy, clinical trials, procedures for symptom relief, and palliative care. Palliative care can be provided alongside cancer-directed treatment. A second opinion at a peritoneal mesothelioma center may help clarify choices.
For a broader overview, see Surgery for Mesothelioma, Mesothelioma Chemotherapy: What to Expect, and Palliative Care for Mesothelioma.
| Option | Role |
|---|---|
| CRS ± HIPEC | Specialist-directed approach for selected peritoneal cases |
| Systemic treatment | Cancer medicines acting throughout the body |
| Clinical trial | Access to research treatment under a study protocol |
| Symptom-directed procedures | May relieve fluid buildup or other problems |
| Palliative care | Addresses symptoms and quality of life at any stage |
Questions and Decision Checklist
Bring a family member or trusted support person to appointments if you wish. Request a written summary of the plan and make sure you understand what would cause the surgeon to change or stop the procedure. You can ask for an interpreter or additional time to decide.
Need help now? Call 800.291.0963 / Live chat 24/7, 365 days a year / Submit Your Case.
| Ask the team | Record the answer |
|---|---|
| Is my diagnosis confirmed by an experienced pathologist? | ________________________ |
| What is the goal of surgery in my case? | ________________________ |
| How likely is complete cytoreduction in my case? | ________________________ |
| Would HIPEC be used, and why? | ________________________ |
| What are my specific risks and alternatives? | ________________________ |
| Who handles urgent problems after discharge? | ________________________ |
Frequently Asked Questions
Is CRS the same as HIPEC?
No. CRS removes visible tumor surgically. HIPEC is chemotherapy circulated inside the abdomen during an operation and is used only when appropriate.
Is CRS used for every type of mesothelioma?
No. This page concerns CRS for peritoneal mesothelioma. Pleural mesothelioma involves different surgical approaches.
Can CRS cure peritoneal mesothelioma?
Surgery can remove visible disease, but microscopic cells may remain and recurrence is possible. Your specialist can discuss the intended goal and uncertainties.
Will I definitely receive HIPEC?
No. Whether HIPEC is suitable depends on the treatment plan, health factors, and findings during surgery.
How long does recovery take?
It varies considerably. The extent of surgery and any complications influence the hospital stay and recovery at home. Ask for a personalized plan.
Does age automatically rule out CRS?
No. Clinicians consider overall health, functional status, disease extent, operative risk, and the patient’s goals.
What if my surgeon cannot remove all visible cancer?
The team may modify or stop the planned procedure if the risks outweigh the likely benefit. Ask beforehand how these decisions are made.
Can I request a second opinion?
Yes. A center experienced in peritoneal mesothelioma can review the diagnosis, imaging, and possible treatment options.
Medical Sources and Further Reading
These primary medical resources offer general information. Treatment plans and current protocols should be confirmed with the patient’s specialist.
Get Help Understanding Your Options
Call 800.291.0963 or use our live chat, available 24/7, 365 days a year.
Submit Your Case — ask about available information and next steps. No particular treatment outcome or legal result is guaranteed.
⚕️ Legal & Medical Information Disclaimer: This page is educational and is not medical or legal advice. Consult qualified oncology and legal professionals about your circumstances. For sudden or severe symptoms, seek emergency medical care.