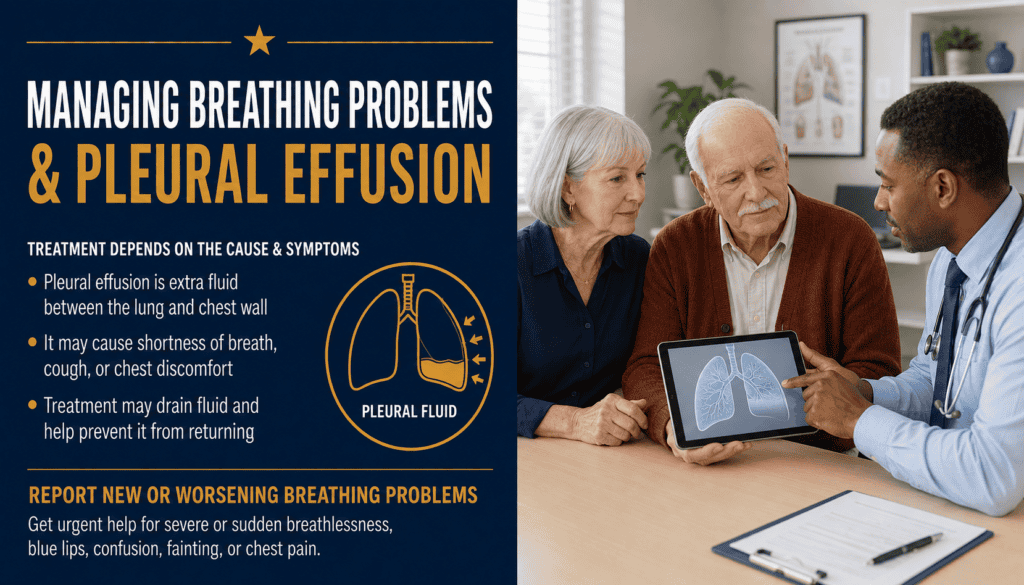
Managing Breathing Problems and Pleural Effusion in Mesothelioma
Symptoms, fluid drainage, recurrence prevention, and practical questions for patients and caregivers.
Shortness of breath in mesothelioma deserves a medical assessment. Fluid around the lung is one possible cause, but cancer-related changes, infection, blood clots, anemia, treatment effects, and other conditions can also contribute. The right response depends on what is causing the symptom—not simply on whether a scan shows fluid.
Why breathing becomes difficult
Pleural mesothelioma affects the lining around the lungs. A pleural effusion is extra fluid between the lung and chest wall; it may compress the lung and cause breathlessness, cough, or chest discomfort. Fluid can be related to cancer, but not every effusion in someone with mesothelioma is malignant. A clinician must consider the complete picture.
| What may contribute | What it can feel like | Why it matters |
|---|---|---|
| Fluid in the pleural space | Breathlessness, cough, chest heaviness | Drainage may help if the fluid is causing symptoms. |
| Tumor-related restriction | Difficulty taking a full breath | Fluid removal may not solve all symptoms. |
| Infection or a blood clot | New or rapidly worsening breathing symptoms | May require urgent, cause-specific treatment. |
| Anemia, heart or lung disease, treatment effects | Fatigue or breathlessness with activity | Needs evaluation rather than assuming fluid is responsible. |
The goal is to improve comfort and function while continuing an individualized cancer-treatment plan. See mesothelioma treatment options for the broader picture.
When breathing symptoms need urgent attention
Call 911 or seek emergency care for sudden or severe trouble breathing, chest pain, fainting, blue or gray lips, or new confusion. Do not wait for a scheduled oncology appointment. These symptoms can have causes beyond a pleural effusion, including potentially dangerous blood clots or infection.
| Situation | Suggested response |
|---|---|
| Sudden, severe breathlessness or chest pain | Call emergency services immediately. |
| New or steadily worsening breathlessness, fever, or a painful/red catheter site | Contact the oncology or pleural-care team promptly; use urgent care if they cannot be reached and symptoms are significant. |
| Mild but persistent change from your usual breathing | Report it to the care team and follow the individualized action plan. |
Patients with an indwelling catheter should follow their own written emergency and drainage instructions. Never exceed a prescribed drainage amount or frequency to try to relieve sudden symptoms.
How clinicians identify the cause
Your clinician may ask when symptoms began, whether they occur at rest, what changes when you sit up, and whether there is fever, chest pain, swelling, or a recent treatment change. Examination and tests are selected for the situation.
| Test or assessment | What it can help answer |
|---|---|
| Oxygen measurement and vital signs | Is there immediate respiratory or circulatory compromise? |
| Chest x-ray or ultrasound | Is fluid present, and where is it located? Ultrasound can guide drainage. |
| CT imaging when appropriate | Are there other chest changes or suspected complications? |
| Pleural fluid analysis | Is infection or malignancy suspected? A negative fluid cytology result does not by itself exclude mesothelioma. |
| Assessment for other causes | Could infection, pulmonary embolism, anemia, or another condition explain the symptoms? |
A fluid sample may be tested, but tissue biopsy and specialist pathology review are often necessary to establish a mesothelioma diagnosis. See mesothelioma biopsy and imaging tests.
Thoracentesis: draining fluid for relief
Thoracentesis, also called pleurocentesis, removes fluid through a needle or small catheter, often with ultrasound guidance. It can relieve pressure and help clinicians determine whether breathlessness improves when fluid is removed. It does not remove the cancer or reliably prevent the fluid from returning.
| Before | During | After |
|---|---|---|
| Review medicines, bleeding risks, allergies, and the procedure plan with your team. | A clinician locates fluid and drains it using sterile technique, commonly with local anesthetic. | The team checks breathing, symptoms, and possible complications; follow discharge instructions. |
Potential complications include bleeding, infection, a collapsed lung (pneumothorax), and rarely lung injury associated with re-expansion. Seek urgent care for significant new chest pain or worsening breathing after the procedure. Learn more at pleurocentesis for mesothelioma.
Managing fluid that comes back
If fluid returns and causes symptoms, the care team may discuss a more durable approach. The decision depends on whether the lung re-expands after drainage, fluid pockets or septations, expected benefits, infection risks, caregiver capacity, and personal preferences.
| Option | When it may be discussed | Important limitation |
|---|---|---|
| Repeat thoracentesis | Temporary relief or selected situations when another procedure is not appropriate. | Fluid can recur and repeat procedures carry risks. |
| Indwelling pleural catheter (IPC) | Recurrent symptomatic effusion, including a lung that does not fully expand. | Requires a sterile drainage plan and monitoring for infection or blockage. |
| Pleurodesis | Recurrent symptomatic fluid when the lung can adequately re-expand. | May not succeed; generally unsuitable when the lung cannot expand. |
| Cancer-directed therapy | When the oncology team expects treatment to help control disease and associated symptoms. | Response is variable; symptoms may still need direct management. |
Professional pleural-effusion guidance supports either an IPC or chemical pleurodesis for appropriate symptomatic patients with an expandable lung, and generally favors an IPC for nonexpandable lung or unsuccessful pleurodesis. This is a shared decision, not a universal rule. Read pleurodesis for mesothelioma.
Breathing support beyond fluid drainage
Even after fluid is drained, breathlessness may persist. Tell your team if you remain short of breath: the cause may be tumor restriction, another lung condition, anemia, infection, anxiety accompanying air hunger, or several factors together. Supportive and palliative care can be provided alongside active cancer treatment.
| Support | Practical use and caution |
|---|---|
| Positioning and pacing | Try an upright supported position, rest between activities, and conserve energy; use the approach your team recommends. |
| Cool airflow or fan | Some patients find airflow across the face soothing; it does not treat low oxygen or an underlying emergency. |
| Supplemental oxygen | Use only when prescribed and according to the clinical plan; not everyone with breathlessness needs oxygen. |
| Medicines and targeted treatment | A clinician may address infection, clot, anemia, airway disease, pain, or persistent air hunger according to its cause. |
| Palliative-care referral | Can help with symptoms, anxiety, practical support, and treatment-goal discussions at any stage. |
Do not start sedatives, opioids, oxygen, or breathing devices on your own. Ask your clinicians which measures are safe for your condition. Hospice care is a separate option for people whose care goals and eligibility fit; palliative care does not automatically mean hospice.
At-home monitoring and caregiver plan
A written plan is especially helpful if breathing symptoms change or a pleural catheter is used at home. Agree on who to call during office hours, after hours, and in an emergency.
| Track | Record or action |
|---|---|
| Breathing pattern | Note what is different from baseline: rest versus activity, new cough, chest pain, or difficulty lying flat. |
| Temperature and other symptoms | Report fever, chills, dizziness, or new confusion promptly. |
| Catheter drainage, if applicable | Follow the prescribed schedule and sterile technique; log amount, appearance, symptoms, and any resistance. |
| Medicines and appointments | Keep an updated list and confirm follow-up after a procedure or treatment change. |
| Caregiver responsibilities | Decide who manages supplies, transport, calls, and written notes—only with the patient’s permission. |
A catheter that stops draining while breathlessness worsens, or a site that becomes red, painful, or produces pus, needs prompt clinical advice. Do not attempt to flush, reposition, or remove it without professional instruction.
Questions for your care team
Bring these questions to the next visit and write down the answers. The most useful plan identifies the likely cause of breathlessness and what to do if symptoms change.
| Ask your team | Why ask |
|---|---|
| Is the effusion the main reason I am short of breath? | Other causes may need separate treatment. |
| Will drainage help, and how will you assess lung expansion? | Helps choose among drainage, IPC, and pleurodesis. |
| If fluid returns, what is the next step? | Avoids repeated uncertainty or unnecessary emergency visits. |
| What risks and recovery should I expect? | Clarifies complications and home support needs. |
| Who do I call if my symptoms worsen at night? | Creates an actionable safety plan. |
| Can supportive or palliative care help now? | Symptom management can accompany oncology treatment. |
For coordinated treatment planning, see your mesothelioma care team and treatment options.
Frequently asked questions
Can mesothelioma cause fluid around the lungs?
Yes. Pleural mesothelioma can be associated with pleural effusion, but other illnesses and treatment effects can also cause fluid. A clinician must determine the cause.
Does draining pleural fluid cure mesothelioma?
No. Thoracentesis treats fluid-related symptoms and may provide a sample for testing; it does not cure the underlying cancer.
Why am I still short of breath after fluid drainage?
Fluid may not be the only cause. Tumor-related restriction, incomplete lung expansion, infection, blood clots, anemia, or other conditions may contribute. Tell your team.
What happens if pleural fluid keeps returning?
Depending on symptoms and lung expansion, clinicians may discuss repeat drainage, an indwelling pleural catheter, pleurodesis, or cancer-directed therapy.
Is pleurodesis better than a pleural catheter?
Neither is best for everyone. Both may be options when the lung expands; a catheter is often favored when it does not. Preferences, risks, and practical support matter.
Can I drain a pleural catheter whenever breathing feels worse?
Follow only your prescribed drainage schedule and limits. New severe breathlessness may be an emergency unrelated to fluid and requires urgent assessment.
Do all patients with breathlessness need oxygen?
No. Oxygen is prescribed based on clinical assessment; other causes and symptom-relief strategies may need attention.
When should I call emergency services?
Call 911 for sudden or severe breathing difficulty, chest pain, fainting, blue or gray lips, or new confusion.
Medical sources and further reading
These resources support the clinical distinctions on this page. Individual treatment decisions require the treating team’s assessment.
Get Help With Mesothelioma Questions
Call 800.291.0963. Live chat is available 24/7, 365 days a year. Submit Your Case to ask about potential legal options. Compensation is not guaranteed. Eligibility and outcomes depend on individual circumstances.
⚕️ Legal & Medical Information Disclaimer
This article is educational, not individualized medical or legal advice. Consult qualified clinicians about symptoms and treatment and an appropriately licensed attorney about legal rights.